Medical Image Sharing Platforms: How to Evaluate and Choose the Right One

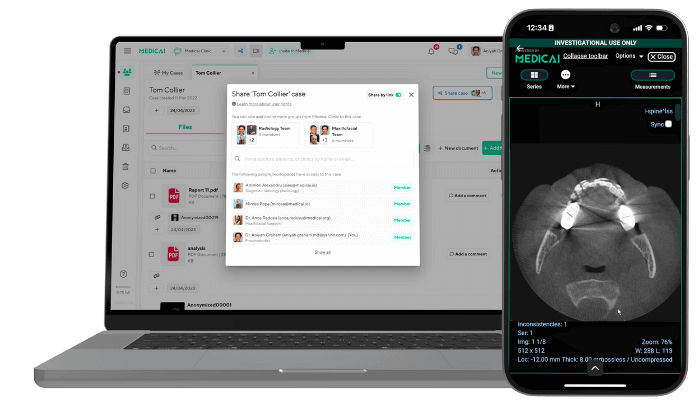
A medical image sharing platform is software that allows healthcare organizations, providers, and patients to securely transmit, receive, and view radiological studies, primarily DICOM imaging from CT, MRI, ultrasound, mammography, and X-ray, across organizational boundaries. The clinical purpose is to eliminate the workflow friction that traditional image sharing methods (physical CD-ROMs, encrypted USB drives, courier-delivered film) introduce into patient care, enabling faster second opinions, smoother specialist referrals, more effective multi-site collaboration, and timely access to prior imaging when patients move between providers.
The market is fragmented. Major categories include patient-facing consumer services (mymedicalimages.com is the dominant traffic-capturing example), enterprise vendor platforms from established radiology IT companies (Intelerad InteleShare, Life Image, Sectra Image Exchange Portal, Nuance PowerShare, Change Healthcare Stratus Imaging Share, eHealth Technologies), Health Information Exchange organizations (CRISP DC, HealtheConnections, regional HIEs across most US states), and cloud-native integrated platforms that combine image sharing with broader PACS infrastructure. Each category serves different buyers, integrates differently with existing imaging infrastructure, and carries different pricing and compliance characteristics.
This guide is designed for healthcare administrators, radiology operations leaders, and IT decision-makers evaluating which medical image sharing platform best fits their organization. It covers the five primary use cases the platforms address, the three categories of platforms available, the ten evaluation criteria that determine procurement fit, a comparison of major platforms in the market, the patient and referrer sharing features that separate the platforms once the procurement boxes are ticked, pricing models, and the implementation considerations that determine whether a deployment succeeds or stalls. For organizations ready to evaluate Medicai’s specific offering, see the Medicai medical image sharing solution.
What Medical Image Sharing Platforms Do: Five Primary Use Cases

Patient Transfer Between Providers
When a patient changes providers, receives a referral, seeks care at a different hospital network, or relocates, their prior imaging needs to follow them. Without an image sharing platform, the standard mechanism remains CD-ROM transfer: the originating facility burns a DICOM CD, the patient hand-carries it to the new provider, and the new provider’s PACS administrator manually imports the studies. The process introduces delays (sometimes weeks), the risk of media loss, and the cost of CD production and staff time for import. Image sharing platforms replace this with cloud-based transfer, delivering prior studies to the receiving provider’s PACS or viewer within minutes.
Second Opinion and Specialist Consultation Sharing
Second opinion radiology, specialist consultations for complex cases, and tumor board review across institutions all require sharing the original imaging studies with another radiologist or clinical team, not just the report. Platforms designed for consultation sharing typically provide both DICOM transmission to the receiving radiologist’s PACS and a viewer link that lets the consulting clinician view the studies in a browser without installing software. Viewer functionality matters because second-opinion radiologists often work across multiple institutions and cannot install vendor software on every workstation they use.
Multi-Site Network Sharing Within Healthcare Organizations
Hospital systems with multiple imaging locations, regional radiology groups serving multiple hospitals, and integrated delivery networks (IDNs) need to share images internally across their sites. The technical requirements differ from external sharing: internal sharing usually involves a much higher study volume, deeper integration with the organization’s RIS and EHR, and the need for consistent identity management so that a patient with the same medical record number is recognized across sites. Most enterprise image sharing platforms can serve this use case, though some are better optimized for internal multi-site use than for external cross-organizational exchange.
Referring Physician Access to Imaging
Referring physicians (primary care doctors, surgical specialists, oncologists, and others who order imaging but do not interpret it themselves) need access to the imaging studies and reports for the patients they refer. Platforms supporting this use case typically provide either a referring physician portal where doctors can search for and view their patients’ studies or direct delivery to the EHR via FHIR DiagnosticReport or similar mechanisms. The platform must handle credentialing and access control across organizational boundaries, and the viewer must work on the kinds of devices referring physicians actually use (mobile devices, tablets, browsers, often without IT support).
Health Information Exchange Participation
Many US states operate Health Information Exchanges (CRISP in Maryland and DC, HealtheConnections in New York, and similar organizations in most other states) that coordinate clinical data sharing within regional healthcare networks. HIE participation increasingly includes imaging exchange, allowing any participating provider to retrieve prior imaging for a shared patient, regardless of where it was originally acquired. Image sharing platforms that integrate with HIEs via standards such as IHE XDS-I.b (Cross-Enterprise Document Sharing for Imaging) can plug into existing HIE infrastructure rather than requiring duplicate exchange agreements.
Categories of Medical Image Sharing Platforms
Medical image sharing platforms fall into three primary categories distinguished by their target buyer, integration model, and clinical scope. Most healthcare organizations end up using at least two categories simultaneously, as the use cases above are not fully served by any single category.
Patient-Facing Consumer Services
Patient-facing image sharing services are subscription- or transaction-based platforms that patients use directly to upload, store, and share their imaging studies with providers of their choice. mymedicalimages.com is the dominant traffic-capturing example, ranking position 2 on the primary US search for “medical image sharing” with 447 monthly organic visits. These services operate as B2C platforms: the patient pays a monthly or per-study fee, uploads their CD-ROM or downloads studies from provider portals, and shares them via email link to a treating physician. The strength of this category is patient autonomy and ease of use; the limitation is that the platform sits entirely outside the healthcare organization’s IT infrastructure and provides no integration with the receiving provider’s PACS, RIS, or EHR.
Enterprise Vendor Platforms
Enterprise vendor platforms are B2B products sold to hospitals, radiology groups, imaging centers, and health systems. The category includes Intelerad InteleShare (which now includes Life Image after Intelerad’s 2022 acquisition of the company), Sectra Image Exchange Portal, Nuance PowerShare (now part of Microsoft following Microsoft’s 2022 acquisition of Nuance Communications), Change Healthcare Stratus Imaging Share (now under Optum), eHealth Technologies, CoActiv Medical, and PaxeraHealth’s CareRAD and CareMD products. These platforms typically offer deep integration with the organization’s existing PACS through DICOM and HL7 protocols, support for cross-enterprise exchange standards (IHE XDS-I.b), and contractual HIPAA Business Associate Agreement terms. Pricing is usually negotiated on annual subscription or per-study contracts, ranging from tens of thousands to hundreds of thousands of dollars per year, depending on study volume and feature scope.
Cloud-Native Integrated Platforms
Cloud-native integrated platforms combine medical image sharing with broader cloud PACS infrastructure rather than treating sharing as a standalone product. The architecture assumes that imaging is already in the cloud (because the underlying PACS is cloud-native), so sharing involves granting external access to a study stored in a cloud archive, rather than transferring the study between systems. Medicai is one example of this approach. Candelis ASTRA Cloud and several smaller cloud-native vendors operate in this space as well. The model fits organizations that are either deploying new imaging infrastructure or migrating from on-premise PACS to the cloud, and it tends to produce lower per-study sharing costs because the marginal cost of a share is small when the imaging is already stored in the cloud.
Ten Criteria for Evaluating Medical Image Sharing Platforms
The following ten criteria are the evaluation framework that buyers should apply before selecting a platform. Each criterion should be addressed with a documented response from the vendor before any procurement decision is made.
| # | Evaluation criterion | What to verify before signing the contract |
|---|---|---|
| 1 | DICOM compliance and supported SOP classes | Does the platform handle all DICOM SOP classes the organization uses, including standard CT and MRI, Mammography (DICOM-MG), Breast Tomosynthesis, Enhanced CT, structured reports, and key images? Are DICOMweb interfaces (WADO-RS for retrieval, QIDO-RS for queries, STOW-RS for storage) supported for cloud-native integrations? |
| 2 | HIPAA compliance and Business Associate Agreement | Is a signed HIPAA Business Associate Agreement provided as a standard contract term? What encryption applies (AES-256 at rest, TLS 1.2 or higher in transit)? What is the breach notification protocol and contractual window? Is the platform vendor HITRUST or SOC 2 Type II certified? |
| 3 | PACS, RIS, and EHR integration | Does the platform integrate with the organization’s existing PACS via DICOM C-STORE or DICOMweb? With the RIS via HL7 ORM and ORU messages? With the EHR via HL7 or FHIR DiagnosticReport? What one-time integration costs and ongoing interface maintenance fees apply? Are integrations included in the base subscription or billed separately? |
| 4 | Cross-enterprise standards support | Does the platform support IHE XDS-I.b for cross-enterprise document sharing of imaging? Is the platform validated under the RSNA Image Share Validation Program? Is the platform integrated with major Health Information Exchanges in the organization’s geographic region? |
| 5 | Viewer capabilities and zero-footprint access | Does the platform include a zero-footprint browser-based DICOM viewer for recipients without their own PACS? Does the viewer support multiplanar reconstruction, measurement tools, window-level adjustment, and basic diagnostic features? Is mobile access (tablet, phone) supported for referring physicians? |
| 6 | Pricing model and total expected cost | What is the pricing model: per-study, per-share, monthly subscription, or annual enterprise contract? What is the total expected annual cost at projected sharing volume? What add-on fees apply for storage retention beyond standard periods, additional users, or premium support? Is there a per-recipient fee for sharing studies externally? |
| 7 | Storage architecture and retention | Where is the data stored: vendor-operated cloud, customer-controlled cloud, or hybrid? Which cloud infrastructure (AWS, Azure, Google Cloud, on-premise)? What is the default retention period and how is retention extended? Are shared studies retained on the platform or only transmitted point-to-point? |
| 8 | Identity management and access control | How does the platform handle user authentication: SSO via SAML, OAuth, or organization-managed credentials? How is access granted to external recipients (referring physicians, specialists, patients)? What audit logging captures who accessed which studies and when? How are inactive accounts disabled? |
| 9 | Workflow ergonomics and adoption | How many clicks does it take a clinician to share a study? Can sharing be initiated from within the PACS workstation, or does it require switching applications? Does the platform support batch sharing for multi-study cases? What is the typical time-to-share for a 200 MB CT study, including upload and recipient notification? |
| 10 | Contract terms and data portability at exit | What is the contract length and renewal structure? What notice period applies for termination? What is the data export process, format (DICOM with full metadata preservation), per-study export fee, and maximum time to complete a full archive export at contract end? Are recipients of previously shared studies notified at contract termination? |
Medical Image Sharing Platforms Compared at a Glance
The table below summarises the major medical image sharing platforms across the dimensions that matter most for procurement evaluation. The information is based on publicly available vendor documentation and SERP data; buyers should verify all details directly with vendors before procurement decisions.
| Platform | Primary buyer type | Architecture | Notable features | Best fit for |
|---|---|---|---|---|
| Medicai | Mid-size imaging centres, specialty practices, cloud-PACS adopters | Cloud-native integrated PACS with image sharing built in rather than bolted on | Combined cloud PACS, zero-footprint DICOM viewer, structured reporting, and image sharing in a single subscription on Microsoft Azure infrastructure | Organisations deploying or migrating to cloud-native imaging where sharing is one workflow among several |
| Intelerad InteleShare (with Life Image) | Enterprise hospital systems, radiology groups | Enterprise B2B platform, integrates with on-premise and cloud PACS | Largest US image exchange network after Life Image acquisition (2022), HIE integrations across most US states, RSNA Image Share validated | Large hospital systems needing the broadest network of exchange partners |
| Nuance PowerShare (Microsoft) | Enterprise health systems, academic medical centres | Cloud platform integrated with Nuance reporting and dictation products | Large established network of participating organisations, integration with Nuance PowerScribe reporting, Microsoft-backed infrastructure since 2022 | Organisations already using Nuance reporting and dictation tools |
| Change Healthcare Stratus Imaging Share (Optum) | Enterprise health systems, payer-integrated networks | Cloud-based enterprise imaging exchange under Optum umbrella | Integration with broader Change Healthcare and Optum revenue cycle ecosystem, enterprise scalability | Health systems already integrated with Optum or Change Healthcare services |
| Sectra Image Exchange Portal | Enterprise hospitals, particularly Sectra PACS customers | Component of Sectra enterprise imaging suite | Deep integration with Sectra PACS, strong in European markets, image exchange for tumour board and specialist consultation | Organisations using or evaluating Sectra enterprise imaging |
| eHealth Technologies | Health systems focused on patient transfer workflows | Service-and-platform hybrid model | Combined technology platform with service operations that retrieve prior imaging from external facilities on behalf of receiving providers | Health systems with high volumes of inbound patient transfers requiring prior imaging retrieval |
| mymedicalimages.com | Patients directly (B2C model) | Consumer cloud service | Patient-controlled imaging access, sharing via email link to providers, no provider IT integration required | Individual patients managing their own imaging, not provider organisations |
Patient and Referrer Sharing Features: What to Compare
The ten criteria above decide whether a platform can be procured. The features below decide whether patients and referring physicians will actually use it. They come up in almost every conversation a clinic has with a sharing vendor, and they are rarely on the data sheet: how a link expires, how a recipient proves who they are, whether a patient can send imaging back, and what happens to the CD burner.
Expiring links and QR codes
A share link is a URL that opens a study in the platform’s browser viewer. Two settings govern its risk. The first is expiry: a link that lives forever is a permanent door into a patient’s imaging, so platforms set a default window (commonly 7 to 30 days) and let the sender shorten it or revoke the link early. The second is scope: whether the link opens one study, the patient’s whole record, or a folder the sender assembled. A QR code is the same link rendered for a phone camera, which matters at the front desk: a patient scans the code on a printed report or a screen and has their study on their phone before they leave the building, without the clinic typing an email address. When evaluating, ask for the default expiry, whether it is configurable per link, whether links can be revoked, and whether the audit log records each open.
Identity: passwords, one-time codes, and invitations
Platforms authenticate link recipients in one of three ways. Password-protected links require the sender to pass a password through a second channel, which works for a referring physician but fails for most patients. One-time-password links send a code by SMS or email at the moment the link is opened, so the recipient proves control of a phone number or inbox without creating an account; this is the model clinics ask for most, because it is the least friction for a patient and still produces an audit record tied to a verified contact. Invitation-based accounts require the recipient to register and, on some enterprise networks, complete two-step verification before the first view; this is the strongest control and the highest abandonment rate for one-off recipients. A platform may offer more than one, and the right question is which model applies to patients and which to referrers.
Patients uploading back to the clinic, and patient-held imaging
Sharing is usually described as outbound, from the clinic to the recipient. The reverse flow is where clinics lose the most staff time: a new patient arrives with a CD or a folder of DICOM files from another provider, and someone has to import it. A patient upload link or portal lets the patient, or the referring practice, send studies and documents into the clinic’s archive before the visit, with the clinic deciding what to accept. The second case is patient-held imaging. A patient whose treatment team is spread across institutions that do not exchange imaging, such as three academic centers in different networks, needs one place to hold their studies and reports and to share them with each center on their own terms. Consumer services charge the patient a monthly fee for this. A clinic-operated patient portal gives the patient the same control at no cost to the patient, because the clinic’s subscription covers it, and the clinic keeps the studies in its own archive.
CD replacement
Replacing CDs is the most common reason a practice buys a sharing platform and the easiest to get wrong in a rollout. A complete replacement covers four flows: patients leave with a link or QR code instead of a disc; referring physicians receive a link to the viewer instead of a courier package; outside studies arrive through an upload link instead of a disc to import; and the few patients and partners who still need physical media get a download of the DICOM files with the viewer included. Budget the rollout around the front desk and the referral coordinator, not the radiologist, since those are the roles that burn and import discs today. Measure discs burned per month before and after; a practice burning 200 discs a month at a few dollars each in media and staff time pays for a sharing subscription from that line alone.
Sharing features compared
The table compares four platforms on the features above, using each vendor’s public documentation on the date shown. “Not stated” means the vendor does not describe the feature publicly, not that it is absent; ask for it in the demo.
| Feature | Medicai | Intelerad InteleShare | PostDICOM | PowerShare (Microsoft) |
|---|---|---|---|---|
| Share by browser link | Yes, opens in the zero-footprint viewer; included in Standard and Enterprise | Yes, Image Share Pages and Web Uploader | Yes, password-protected share links on every plan | Yes, invitation-based; recipient creates an account |
| Link expiry | [Default X days, configurable per link / fixed] | Not stated | Not stated | Not stated |
| QR code for patients | [Yes / No] | Yes, patient reach via QR code through Epic MyChart, Cerner, Athena portals | Not stated | Not stated |
| One-time code by SMS or email | [Yes / No] | Not stated | Not stated; links are password-protected | Two-step verification at login (SMS code, US only, or authenticator app) |
| Patient portal | Yes, Medicai Patient Portal on Standard and Enterprise | Through the health system’s EHR portal (MyChart and others) | Patient access via share link; no portal named | Patient account by facility invitation |
| Patient or referrer upload to the clinic | [Yes via Patient Portal / upload link; plan] | Yes, Study Upload and patient submission through MyChart | Yes, secure upload link for patients and external parties on Premium and Enterprise | Yes, at participating facilities (Easy Uploader) |
| CD replacement | Link, QR [if confirmed], upload link, and DICOM download | “Ditch the Disk” program; upload from local media | Browser viewing with no CD; upload link | Patient upload at facilities replaces CDs |
| Cost to the patient | None; covered by the clinic’s subscription | None stated | None stated | None stated |
| Pricing published | Yes, from $249 a month | No | Yes, from EUR 79 a month | No |
For the Medicai column in detail, see the Medicai medical image sharing solution and the medical imaging exchange product page.
Pricing Models for Medical Image Sharing Platforms
Medical image sharing platforms use four distinct pricing models. Understanding which model the platform applies is essential for projecting a realistic total cost at the organization’s expected sharing volume.
Per-study or per-share pricing. The platform charges a per-transaction fee, typically ranging from $2 to $15 per shared study, depending on volume and contract terms. This model is most common among enterprise platforms with large, established networks (e.g., Intelerad InteleShare, Nuance PowerShare). It scales linearly with use, which is predictable for high-volume organizations but can be expensive at scale. A health system sharing 50,000 studies per year at $5 per study faces an annual cost of $250,000 in sharing fees alone, before subscription or integration costs.
Monthly or annual subscription. Subscription pricing covers unlimited sharing within a defined feature scope, with monthly costs ranging from a few hundred dollars for small practices to tens of thousands for large enterprise deployments. This model fits organizations with high or variable sharing volume because the per-study cost effectively decreases as volume increases. Cloud-native integrated platforms often use this model because the underlying infrastructure costs scale differently from per-transaction infrastructure costs.
Enterprise contract pricing. Large health systems typically negotiate custom enterprise contracts that bundle image sharing with broader services: integration with the organization’s PACS, RIS, and EHR; HIE participation fees; premium support; and extended retention. Annual enterprise contracts for large health systems range from $100,000 to several million dollars, depending on scope and study volume. The negotiation typically includes the implementation of professional services as a one-time cost component.
Patient-pay or service-based pricing. Patient-facing services (mymedicalimages and similar) charge the patient directly, typically with a monthly subscription ($10 to $20 per month) plus per-study upload or download fees. Service-and-platform hybrid vendors (eHealth Technologies) charge the receiving healthcare organization on a per-case basis for retrieval-as-a-service, where the vendor’s operations team actively retrieves prior imaging from external facilities on behalf of the receiving provider.
Pricing transparency varies widely across the category. Some vendors publish pricing tiers publicly (Medicai’s cloud PACS subscription pricing is published on the website); most enterprise vendors require a sales engagement to receive any pricing information, with the actual cost depending on negotiation, study volume, and feature scope.
Implementation Considerations
The platform decision is only one part of a successful deployment. The implementation work that follows determines whether the platform delivers the operational benefit on which the procurement decision was based or stalls due to integration friction. Five specific considerations recur in deployments.
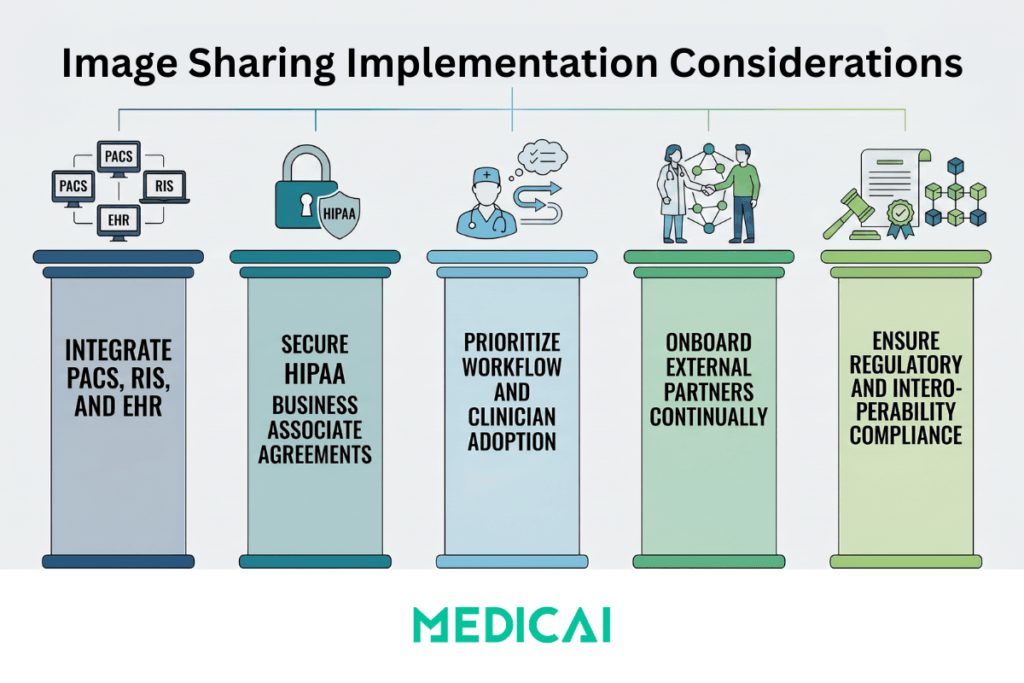
PACS, RIS, and EHR integration scope. Most medical image sharing platforms require integration with the organization’s existing PACS (for DICOM transmission), RIS (for worklist coordination and report delivery), and EHR (for clinical context and order management). Integration through HL7 ORM and ORU messages, FHIR DiagnosticReport, and DICOMweb interfaces is mature but requires time for interface engineering. Budget integration as a one-time professional services cost of $25,000 to $150,000, depending on scope and the number of integrations required.
HIPAA Business Associate Agreement scope. Every vendor in the data flow that touches PHI is a Business Associate under HIPAA. For image sharing platforms, this includes the platform vendor itself and any sub-processors (cloud infrastructure providers, third-party viewer vendors, identity providers). The BAA must cover the full chain and must include the breach notification, audit, and termination provisions required by 45 CFR 164.504(e). Legal review of the BAA terms is a non-negotiable step before signing.
Workflow training and clinician adoption. An image sharing platform that requires clinicians to switch applications, log in separately, navigate multiple menus, and follow non-obvious workflows will see low adoption regardless of its technical capabilities. Training should focus on the specific workflows the platform replaces (CD burning, FedEx shipping, manual import) and the time savings each workflow change produces. Adoption typically lags deployment by 3 to 6 months as users learn to make the new workflow their default.
External partner onboarding. Image sharing platforms only deliver value when the parties exchanging images both use compatible systems or when the platform’s network includes the relevant partners. Onboarding external referring physicians, specialist consultants, and patient transfer destinations onto the platform typically requires per-partner outreach, credentialing, and training. Plan for this as an ongoing operational activity rather than a one-time deployment task.
Regulatory and interoperability compliance. The 21st Century Cures Act information blocking provisions prohibit healthcare organizations from engaging in practices that interfere with the access, exchange, or use of electronic health information, including imaging. Image-sharing platform selection and deployment should be reviewed against information-blocking obligations, particularly where the chosen platform creates barriers to sharing with non-participating providers.
Frequently Asked Questions
A medical image sharing platform is software that allows healthcare providers, organizations, and in some cases patients to securely transmit, receive, and view radiological imaging studies (DICOM data from CT, MRI, ultrasound, mammography, X-ray, and other modalities) across organizational and geographic boundaries. The clinical purpose is to replace traditional image sharing methods, such as CD-ROMs and physical media, with secure electronic exchange that is faster, more reliable, and integrated with the organization’s PACS, RIS, and EHR systems. Major platforms include Intelerad InteleShare, Nuance PowerShare, Change Healthcare Stratus Imaging Share, Sectra Image Exchange Portal, eHealth Technologies, and cloud-native platforms such as Medicai.
Pricing varies widely by model and platform. Per-study pricing on enterprise platforms typically ranges from $2 to $15 per shared study, producing annual costs of $50,000 to $500,000+ for high-volume health systems. Monthly subscription pricing for mid-size organizations ranges from a few hundred to tens of thousands of dollars per month, depending on the scope of features. Enterprise contracts for large health systems range from $100,000 to several million dollars annually, including integration and support. Patient-facing consumer services (mymedicalimages and similar) charge patients directly at $10 to $20 per month for a subscription, plus per-study fees. Most enterprise vendors require a sales engagement to receive pricing information; some cloud-native platforms publish subscription pricing publicly.
HIPAA compliance is a contractual requirement for any platform handling US patient imaging data. Required elements include a signed HIPAA Business Associate Agreement from the platform vendor, AES-256 encryption of DICOM data at rest, TLS 1.2 or higher encryption for data in transit, role-based access controls restricting study access to authorized users, and complete audit logging of all study access events. Healthcare organizations must verify that the BAA scope includes any sub-processors (such as cloud infrastructure providers, viewer vendors, and identity providers) that handle PHI. Some platforms hold additional certifications, including SOC 2 Type II and HITRUST CSF, which provide independent verification of security controls beyond those required by the HIPAA BAA.
Medical image sharing platforms typically support multiple imaging and clinical data standards. DICOM is the foundational standard for medical imaging data structure and transmission, with DICOMweb (WADO-RS, QIDO-RS, STOW-RS) providing modern HTTP-based interfaces for cloud-native integration. IHE XDS-I.b (Cross-Enterprise Document Sharing for Imaging) defines the cross-enterprise exchange protocol used by Health Information Exchanges and large imaging networks. HL7 ORM and ORU messages handle order management and report delivery between the platform and RIS or EHR systems. FHIR DiagnosticReport provides modern API-based integration for newer EHR deployments. The RSNA Image Share Validation Program certifies platforms that meet specific interoperability standards for image exchange.
Medical image sharing platforms integrate with existing PACS systems through standard DICOM protocols and DICOMweb interfaces. The most common integration architecture uses DICOM C-STORE to receive studies from the PACS into the sharing platform and DICOMweb WADO-RS to retrieve shared studies into recipient PACS systems. Modern cloud-native platforms commonly use DICOMweb end-to-end, eliminating the need for VPN configuration or static IP addressing between organizations. Integration with the RIS for worklist coordination uses HL7 ORM and ORU message exchange, while EHR integration for clinical context uses HL7 ORU or FHIR DiagnosticReport, depending on the EHR’s supported standards. Verify before contracting which specific PACS, RIS, and EHR systems the platform has certified integrations with, and whether integration is included in the standard subscription or billed as a separate professional services engagement.
Yes. Patients have several options for sharing their own imaging studies with providers. Patient-facing consumer services such as mymedicalimages.com allow patients to upload their imaging (typically from a CD-ROM provided by the imaging facility) and share it via secure link to treating physicians. Many hospital patient portals allow patients to download or share imaging directly with external providers. The 21st Century Cures Act includes patient access provisions that strengthen patients’ rights to access their own imaging in electronic form. For routine sharing between treating providers (rather than patient-initiated sharing), enterprise platforms operated by the providers themselves are typically the more efficient mechanism.
A clinic-operated patient portal, such as the Medicai Patient Portal, combines the two: the patient controls who sees their studies and the clinic’s subscription covers the cost.
Most cloud platforms issue browser links with a configurable expiry and can render the link as a QR code for a patient’s phone. [Medicai links expire after X days by default and can be set per link; QR codes are generated from the viewer.] Intelerad InteleShare reaches patients by QR code through the health system’s portal. PostDICOM and PowerShare do not state an expiry window publicly; ask for it in the demo and ask whether links can be revoked early.
Yes, in two ways. Consumer services such as mymedicalimages.com give the patient an account for $10 to $20 a month plus per-study fees, with no connection to any provider’s systems. A clinic-operated patient portal gives the patient the same control at no cost to them: the clinic’s subscription covers it, the studies stay in the clinic’s archive, and the patient shares a link with each center. If the centers are in different networks that do not exchange imaging, the second route is the one that works, because it does not depend on the centers joining the same exchange.
One-time codes verify the recipient at the moment of opening without an account. [Medicai: state OTP by SMS and email, and patient upload through the Patient Portal, with the plan.] PowerShare uses two-step verification on a registered account. PostDICOM offers a secure upload link for patients and external parties on its Premium and Enterprise plans. InteleShare accepts patient submissions through the health system’s EHR portal.
The Cloud-Native Alternative
The medical image sharing platform market evolved from the assumption that sharing is a distinct workflow from primary imaging storage and interpretation: imaging lives in the organization’s PACS, and a separate platform handles sharing copies of those studies with external recipients. Cloud-native imaging infrastructure changes this assumption. When imaging is already stored in the cloud, sharing becomes a matter of granting access to a study rather than transferring a copy between systems.
The architectural difference produces operational differences. Setup time is shorter because no point-to-point transfer infrastructure is required. Per-share costs are lower because the marginal cost of granting access is small compared to the cost of transferring large DICOM files. Viewer integration is more consistent because the same viewer that the organization’s own clinicians use is available to external recipients through the same browser-based interface. And the line between internal multi-site sharing and external cross-organizational sharing blurs, as both rely on the same access-control mechanism applied to studies within the same cloud archive.
Medicai’s approach combines cloud PACS, vendor-neutral archive, zero-footprint DICOM viewer, structured reporting, and image sharing as integrated components of a single platform on Microsoft Azure infrastructure. The same DICOM Gateway that receives studies from the modality also makes them available for sharing. The same zero-footprint viewer that the organization’s radiologists use is the viewer that external referring physicians and specialists access through secure links. The HIPAA Business Associate Agreement covers the full data flow within a single vendor relationship rather than across multiple vendors in a chain. For organizations evaluating image sharing as part of a broader cloud imaging strategy, see the Medicai medical image sharing solution and the Medicai cloud PACS for the underlying infrastructure that supports the integrated approach.


Related Articles
Lets get in touch!
Learn more about how Medicai can help you strengthen your practice and improve your patients’ experience. Ready to start your Journey?
Book A Free Demo