Radiology Voice Recognition Systems and Dictation Software: How the Reading Workflow Works in 2026

Radiology dictation software, voice recognition, and worklist management are three connected components of the radiologist’s daily reading workflow. Worklist management determines which studies the radiologist reads next and in what order. Voice recognition translates the radiologist’s dictation into structured text. Dictation software hosts the voice recognition engine, integrates with the PACS viewer, and produces a structured report delivered to the ordering physician. Together, the three components define how productively a radiologist can move from “study arrives in the system” to “signed report delivered to the EHR.”
A few large vendors dominate the market for each of these three components, with a growing layer of AI-first reporting platforms entering the space since 2022. Named products include Nuance PowerScribe and PowerScribe One (now part of Microsoft following the 2022 Nuance acquisition), 3M MModal Fluency for Imaging and Fluency Direct, Nuance Dragon Medical One, and a newer generation of AI-assisted reporting tools, including Rad AI Reporting and Impressions, MD.ai, rScriptor, and VoiceboxMD. PACS and RIS platforms increasingly build worklist management directly in, rather than offering it as a separate product, with cloud-native platforms making integrated worklist orchestration a standard feature.
This guide covers the complete picture: how the reading workflow connects worklist, voice recognition, and dictation; what the major dictation software products do and how they differ; how voice recognition technology has evolved with AI-assisted scribes; how worklist management has changed with AI triage; how these components integrate with PACS, RIS, and EHR systems; and what radiology practices should evaluate before procurement. For broader AI applications in radiology, including CAD, triage, segmentation, reporting, and workflow automation, see AI in radiology.
The Radiology Reading Workflow: From Worklist to Final Report
A radiologist’s productivity depends on how efficiently studies move through four sequential workflow stages. The reading workflow is not a single tool. It is a pipeline of connected systems, each handling one stage, with the pipeline’s overall productivity determined by the slowest stage and the friction between stages.
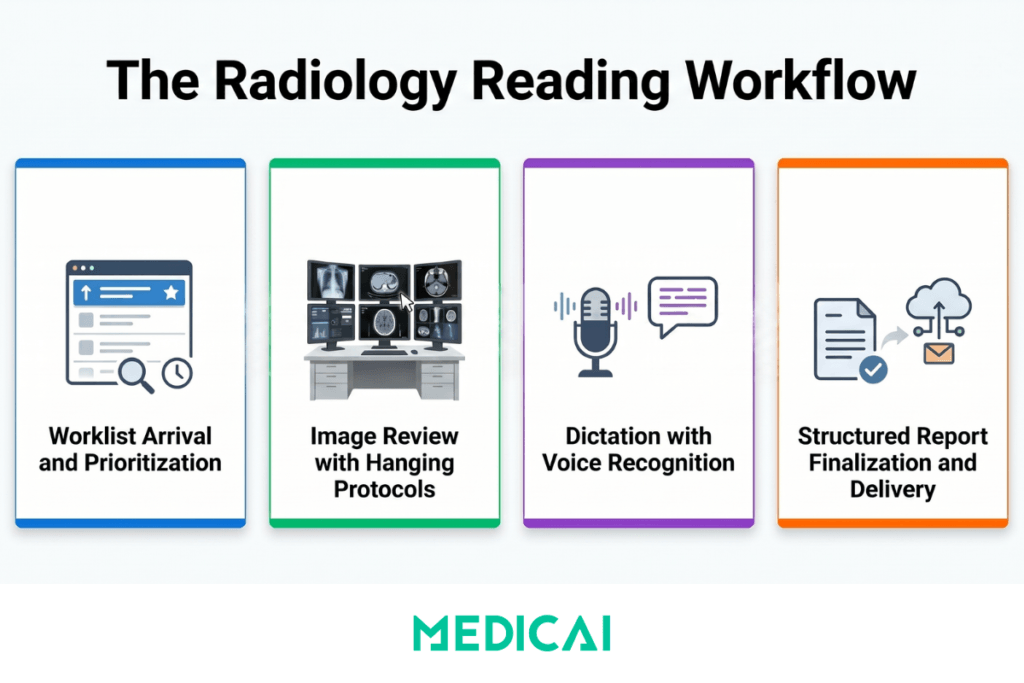
Stage 1: Worklist arrival and prioritization. Studies arrive at the radiologist’s worklist after acquisition at the imaging modality. The worklist is the radiologist’s queue of studies awaiting interpretation, typically populated from the RIS (Radiology Information System) and presented through the PACS or a dedicated worklist orchestrator. Modern worklists support filtering by modality, body part, urgency, subspecialty, and ordering provider; AI triage may reorder the worklist based on case-level suspicion scores, moving studies with suspected critical findings to the top before the radiologist opens any study.
Stage 2: Image review with hanging protocols. The radiologist opens the study from the worklist, and the PACS displays the images according to the configured hanging protocol for that study type. Hanging protocols determine which series appear on which monitor, their window-level settings, and which comparison priors are used. Configurable hanging protocols separate efficient from inefficient reading workflows; the Medicai hanging protocols cover these principles.
Stage 3: Dictation with voice recognition. While reviewing the images, the radiologist dictates findings into a microphone connected to the dictation software. The voice recognition engine transcribes speech into text in real time, using radiology-specific vocabulary, anatomical terms, and common phrase patterns to produce accurate transcription. Modern dictation software integrates with structured reporting templates (RSNA RadReport, BI-RADS for mammography, Lung-RADS for lung screening, and so on), so the dictated content populates structured fields rather than producing a free-text dump.
Stage 4: Finalize and deliver the structured report. The radiologist reviews the transcribed text, makes any necessary edits, applies the structured report template, and signs the report. The signed report is delivered to the ordering physician’s EHR through HL7 ORU integration, attached to the imaging study in the PACS archive, and made available for downstream workflows, including patient notification, billing, and quality assurance review. Structured radiology reporting covers the depth of structured reporting.
Each stage has its own software, vendor ecosystem, and procurement decision. Each stage also has integration points with the stages before and after it, and the quality of these integrations determines whether the pipeline runs smoothly or the radiologist spends time navigating between systems instead of reading studies.
Radiology Dictation Software: The Product Landscape
Radiology dictation software falls into three categories distinguished by architecture, target buyer, and integration model. Most US radiology practices use a single product from the enterprise-integrated category, sometimes augmented by an AI-first reporting tool for specific subspecialties or use cases.
Enterprise Integrated Reporting Platforms
Enterprise integrated platforms combine voice recognition, dictation, structured reporting, report editing, and EHR delivery into a single product that integrates deeply with PACS and RIS. Two products dominate this category.
Nuance PowerScribe and PowerScribe One are the dominant US radiology reporting platforms, used by most US radiology groups. The product evolved from PowerScribe 360, with PowerScribe One representing the current cloud-native generation. PowerScribe integrates with most major PACS systems via DICOM and HL7 interfaces, supports structured reporting templates, including RSNA RadReport, and is part of the broader Microsoft Nuance Healthcare suite following Microsoft’s 2022 acquisition of Nuance Communications. PowerScribe’s voice recognition engine is calibrated on extensive radiology dictation corpora, achieving high accuracy for radiology vocabulary with a relatively short setup time per radiologist.
3M MModal Fluency for Imaging (with its dictation companion, Fluency Direct, used more broadly across clinical specialties) is the second major enterprise platform in this category. 3M’s healthcare division acquired Fluency for Imaging and later divested it as part of 3M’s healthcare separation into Solventum. The product offers core capabilities similar to PowerScribe, with deeper natural language understanding features that extract structured data from free-form dictation and automatically populate report templates.
AI-First Reporting Platforms
AI-first reporting platforms started from a different design assumption than enterprise-integrated platforms. Rather than treating voice recognition as the central feature with AI as an added layer, these platforms treat AI-drafted report content as the central feature, with voice recognition providing editing and correction input. The category emerged after 2022 as large language models matured for clinical text generation, and it has grown rapidly through 2025.
Rad AI Reporting and Rad AI Impressions represent the most established products in this category. Rad AI Impressions produces an AI-drafted impression section based on the radiologist’s findings, which the radiologist reviews, edits, and signs. Rad AI Reporting extends this to broader report generation. The product ranks position 2 in US search results for “radiology dictation software,” indicating strong commercial visibility and adoption velocity.
Cloud PACS vendors have started to build drafting into the reading environment rather than selling it as a separate product. Medicai’s Radiology AI Co-Pilot runs inside the Medicai DICOM viewer: the radiologist dictates, the Co-Pilot maps the findings into the sections of the chosen template (history, technique, comparison, findings), drafts an impression from the radiologist’s own findings, marks every AI-added passage in brackets, and runs a proofreading pass before signing. It works with the practice’s own templates, including templates in languages other than English, and the radiologist reviews and signs every report. It does not analyze images. For a practice that is moving to a cloud PACS anyway, this removes the separate dictation contract and the viewer-to-dictation integration described later in this guide.
Standalone Dictation Tools
Standalone dictation tools serve a different buyer: independent radiologists, teleradiology contractors, and small radiology practices that need dictation capability without procuring an enterprise platform. VoiceboxMD is one example in this category, offering dictation and structured reporting at per-radiologist subscription pricing rather than enterprise-contract pricing. The category generates lower total revenue, but it serves a segment of the radiology market that enterprise platforms cannot serve economically.
The category also includes consumer-grade tools that some radiologists use for supplementary dictation, such as Nuance Dragon Medical One (the broader clinical dictation product used across multiple specialties), Otter.ai, and similar tools. These are not designed for radiology-specific structured reporting, but radiologists sometimes use them as workarounds in environments without dedicated dictation software.
Radiology Voice Recognition Systems: How They Work and Which Systems Lead
Radiology voice recognition systems are speech recognition engines trained specifically on radiology dictation to transcribe a radiologist’s spoken findings into structured report text in real time. The leading radiology voice recognition systems in the US are Nuance PowerScribe and PowerScribe One (Microsoft) and 3M MModal Fluency for Imaging (Solventum), both enterprise platforms that pair voice recognition with structured reporting and EHR delivery; Nuance Dragon Medical One provides cross-specialty clinical voice recognition used alongside them.
A newer generation of AI-first systems, led by Rad AI, uses voice recognition as the edit-and-correction layer on top of AI-drafted report content rather than as the primary input. What separates a radiology voice recognition system from general speech recognition is radiology-specific vocabulary training, real-time structured-template population, and accurate classification of phrases such as BI-RADS and Lung-RADS, with vendor-reported word accuracy typically exceeding 99% for trained users.
Voice recognition in radiology is not the same technology as the general-purpose speech recognition used in consumer products. The vocabulary differs, accuracy requirements are higher, and integration with structured reporting templates is more demanding than general clinical or consumer use cases. Three properties distinguish radiology-grade voice recognition.
Radiology-specific vocabulary training. Radiology dictation includes anatomical terms, pathological terms, measurement units, modality terms, and standardized classification phrases (Lung-RADS 4B, BI-RADS 3 with downgrade to BI-RADS 2 on follow-up, TI-RADS 5 with biopsy recommendation) that general speech recognition systems treat as noise. Radiology voice recognition engines are trained on large corpora of radiology dictation to transcribe these terms accurately; this training and adaptation yield dramatically higher accuracy than general speech recognition on the same audio. Vendor-reported accuracy for radiology dictation typically exceeds 99% word accuracy for trained users, with the remaining errors concentrated in proper nouns, drug names, and ambiguous medical abbreviations.
Real-time transcription with structured template population. Modern radiology voice recognition transcribes speech in real time (not in batch later), so the radiologist sees the transcribed text appear in the report editor as they dictate. The transcription engine identifies report section markers (“findings:”, “impression:”, “comparison:”) and routes the dictated content to the corresponding section of the structured template. Measurement extraction is increasingly automated: when the radiologist dictates “the right kidney measures 11.2 by 4.8 centimeters,” the dictation software extracts the numeric values and populates the structured measurements field, rather than writing only free text.
AI-assisted draft generation beyond transcription. The newest generation of radiology dictation software does not just transcribe what the radiologist says. AI scribe products generate draft report content from the imaging study itself, which the radiologist reviews and edits using voice commands. The architectural distinction matters: traditional voice recognition is human-driven (the radiologist speaks, the software transcribes), while AI scribe products are software-driven with human review (the software drafts, the radiologist verifies). The structured reporting guide covers the trust framework for AI-generated reporting, including RAG-enhanced generation, evaluation metrics, and human-in-the-loop oversight.
The clinical evidence base for AI-assisted reporting continues to develop. Research published in RadioGraphics on RAG-enhanced GPT-4 in trauma radiology demonstrated 100% diagnostic accuracy and 96% classification accuracy on benchmark cases when the AI was augmented with retrieval from validated clinical knowledge bases. The evidence supports the architectural pattern (RAG-enhanced AI with cited sources and clinician oversight) over any specific vendor product, and the practical implication is that AI-first reporting platforms are evolving so rapidly that the buyer evaluation should focus on the architecture and update cadence rather than solely on the current feature set.
Worklist Management: The Gateway to the Reading Workflow
The worklist is the radiologist’s queue of studies awaiting interpretation. It is the entry point of the entire reading workflow, and the rest of the workflow’s productivity depends on the worklist being populated, prioritized, and presented correctly to the right radiologist at the right time.
RIS Worklist Versus PACS Worklist Versus Orchestrator
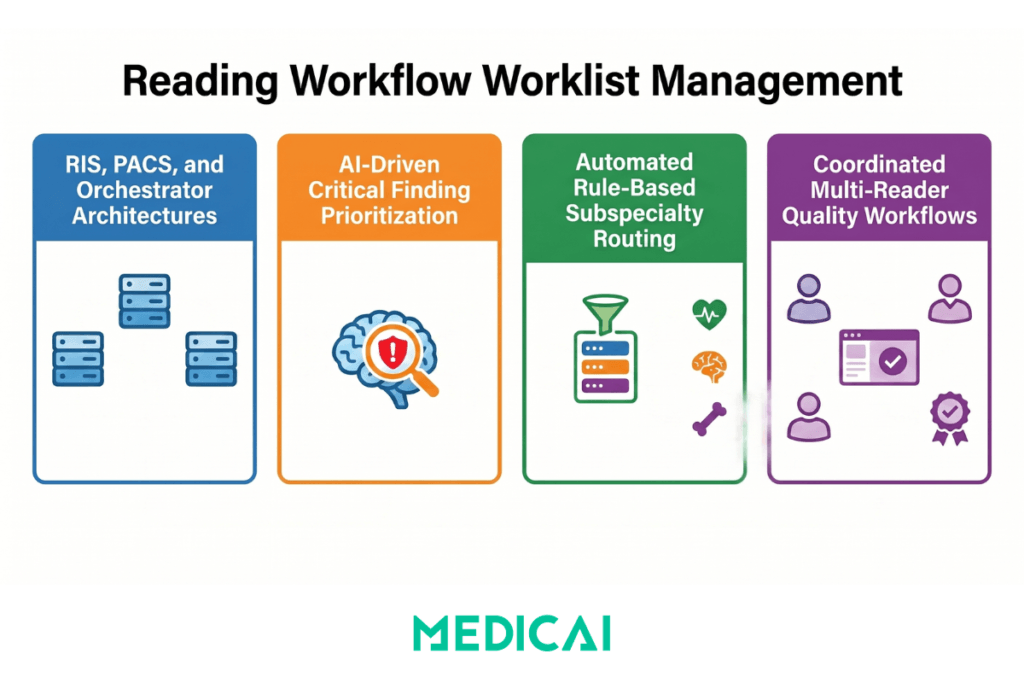
Three architectural patterns for radiology worklist management exist in the US market. The RIS-driven worklist originates from the Radiology Information System, which manages orders, scheduling, and report tracking. The RIS pushes studies to the radiologist’s worklist as they arrive, typically via HL7 ORM messages consumed by the PACS or worklist client. This is the traditional architecture and is still common in established hospital deployments.
In a PACS-driven worklist, the PACS originates the worklist, with studies appearing as DICOM C-STORE operations complete from the imaging modalities. The PACS handles filtering, sorting, and assignment without a round-trip to the RIS. Cloud-native PACS platforms may not have a separate RIS in the deployment at all.
The orchestrator worklist combines studies from multiple sources (RIS, PACS, third-party AI triage, external referrals) into a single unified worklist presented to the radiologist. Orchestrator products, including Primordial (now part of Nuance), Recurve, and integrated capabilities within modern PACS platforms, address the multi-source worklist problem common in distributed reading environments, teleradiology networks, and large hospital systems with multiple imaging sites.
AI Triage and Worklist Prioritization
AI triage has transformed worklist management since 2020. The traditional worklist sorts studies by arrival time, the ordering physician’s priority flag, or modality category. AI triage adds case-level malignancy or critical-finding scores, produced by AI processing before the radiologist opens the study, moving studies with suspected stroke, intracranial hemorrhage, pulmonary embolism, pneumothorax, or other time-sensitive findings to the top of the worklist regardless of arrival time.
Named AI triage products, including Viz.ai for stroke, Aidoc for multi-pathology triage, and RapidAI for stroke and pulmonary embolism, integrate with the worklist through DICOM Structured Reports, HL7 messaging, or vendor-specific APIs that the worklist orchestrator consumes. The clinical and operational impact is covered in the AI in radiology guide. From a worklist perspective, the practical implication is that the worklist must receive and act on AI triage signals, rather than treating them as a static FIFO queue.
Subspecialty Routing and Multi-Reader Workflows
Subspecialty routing assigns studies to radiologists with the appropriate subspecialty training: pediatric studies to pediatric radiologists, breast imaging to breast radiologists, neuro studies to neuroradiologists, and cardiac imaging to cardiac radiologists. The routing logic is typically rule-based (study type and body part determine subspecialty assignment), and the worklist orchestrator implements the routing automatically rather than requiring manual reassignment by reading room staff.
Multi-reader workflows in which two radiologists read the same study (population screening programs, peer review, second-opinion review) require worklist coordination to ensure that both readers see the study, that neither reader’s interpretation is biased by the other’s report, and that the comparison of the two reports is tracked for quality assurance. The MASAI trial described in the AI in mammography guide illustrates a multi-reader workflow in population breast cancer screening, with AI as one of the two readers.
Radiology Dictation and Workflow Tools Compared at a Glance
| Product | Category | Primary capability | Vendor and ownership | Best fit for |
|---|---|---|---|---|
| Nuance PowerScribe / PowerScribe One | Enterprise integrated reporting platform | Voice recognition, structured reporting, EHR integration, broad PACS compatibility | Microsoft (acquired Nuance Communications in 2022) | Most US radiology groups and hospital systems; the de facto market standard for enterprise reporting |
| 3M MModal Fluency for Imaging | Enterprise integrated reporting platform | Voice recognition, NLP-based structured data extraction, broad imaging integration | Solventum (3M Healthcare separation, 2024) | Health systems with existing 3M MModal investment or preference for NLP-driven data extraction |
| Rad AI Reporting and Impressions | AI-first reporting platform | AI-drafted impressions and report sections, voice editing, integration alongside existing dictation | Rad AI (independent vendor) | Radiology groups looking to reduce report drafting time using AI-generated impressions, often deployed alongside an existing enterprise platform |
| Medicai Radiology AI Co-Pilot | AI-assisted reporting built into a cloud PACS viewer | Dictation to structured draft in the practice’s templates, impression drafting, AI text marked in brackets, proofreading before signing; no image analysis | Medicai | Practices and teleradiology groups on, or moving to, Medicai Cloud PACS that want drafting without a separate dictation contract |
| rScriptor | Reporting and dictation platform | Radiology-focused dictation, reporting, and PACS integration at competitive pricing | Scriptor Software (independent vendor) | Small and mid-size radiology practices seeking an alternative to enterprise platform pricing |
| VoiceboxMD | Standalone dictation tool | Per-radiologist dictation and reporting without enterprise contract | VoiceboxMD (independent vendor) | Independent radiologists, teleradiology contractors, small practices needing per-seat pricing |
| Nuance Dragon Medical One | General clinical dictation (not radiology-specific) | Cross-specialty clinical voice recognition for EHR documentation | Microsoft (Nuance) | Health systems standardising on a single dictation engine across all clinical specialties, supplementing radiology-specific tools rather than replacing them |
For Medicai specifically: the Radiology AI Co-Pilot does not analyze images and is not marketed as a medical device. Image-analysis AI (for example, a cleared mammography detection model) connects to the workflow through AI Integrations, and the tool’s vendor holds clearance for that function and its indication. The next section shows how that connection works.
PACS Workflow Integration: How the Components Connect
The four reading workflow stages (worklist, image review, dictation, report) operate through different vendor systems in most US radiology deployments. System integration determines whether the workflow runs as a smooth pipeline or as a series of context switches that consume radiologist time without increasing reading throughput.
Worklist Integration with PACS and RIS
The worklist receives study information from the RIS (orders, scheduling, ordering provider context) via HL7 ORM messages and from the PACS (study arrival confirmation, image counts, modality details) via DICOM or HL7 messages. The integration must reconcile information from both sources so the worklist shows the correct studies with the correct ordering context. In cloud-native PACS deployments without a separate RIS, the PACS itself manages the worklist directly, eliminating the integration complexity.
Image Viewer Integration with Dictation
The PACS viewer and the dictation software must communicate so the radiologist can navigate from the worklist to the study to the dictation context without manual context switching. The standard integration pattern uses URL or messaging hooks: when the radiologist opens a study in the PACS viewer, the dictation software opens the corresponding report template; when the radiologist completes the dictation, the report is associated with the study in the PACS archive. Integration depth varies widely across vendor combinations, and radiologist productivity depends heavily on how well the two systems communicate.
Report Delivery via HL7 ORU
The dictation software delivers the signed structured report to the EHR and PACS via HL7 ORU messages. The ORU message includes the report text, structured data fields, the signing radiologist’s identity, the report status (preliminary, final, addendum), and a reference to the imaging study. The EHR ingests the ORU message and makes the report available in the patient’s chart; the PACS ingests it and associates it with the study in the imaging archive for future retrieval.
FHIR DiagnosticReport for Modern EHR Integration
Newer EHR deployments use FHIR DiagnosticReport as the API-based alternative to HL7 ORU for report delivery. FHIR provides a more structured, queryable report representation that downstream applications can consume programmatically. Cloud-native PACS and reporting platforms increasingly support both HL7 ORU and FHIR DiagnosticReport, with the choice determined by the receiving EHR’s supported standards.
Connecting a third-party AI model: the mammography example
A practice that wants a cleared detection model, such as Lunit INSIGHT MMG for mammography or INSIGHT CXR for chest radiography (both FDA 510(k)- cleared and CE-marked for their stated indications), does not integrate the model with the dictation software. It integrates it with the PACS, and the result reaches the radiologist in the viewer before dictation starts. The pattern is the same whichever cloud PACS and whichever model:
- Routing rule. The PACS is configured to send every study that matches a rule (modality MG, a specific procedure code, a specific site) to the model as it arrives. On Medicai, this rule sits in the DICOM Gateway configuration.
- Transport. The study goes to the model’s endpoint, in the vendor’s cloud or on a local inference server, by DICOM C-STORE or DICOMweb, under a data processing agreement or BAA between the practice and the AI vendor.
- Results. The model returns DICOM objects attached to the original study: a structured report (SR) with findings and scores, a secondary capture or GSPS overlay with marks on the image, or both.
- Display. The viewer shows the returned objects alongside the images, so the radiologist sees the model’s marks in the reading session without opening another application.
- Worklist. Optionally, a positive result raises the study’s priority in the worklist (the triage pattern described earlier in this guide).
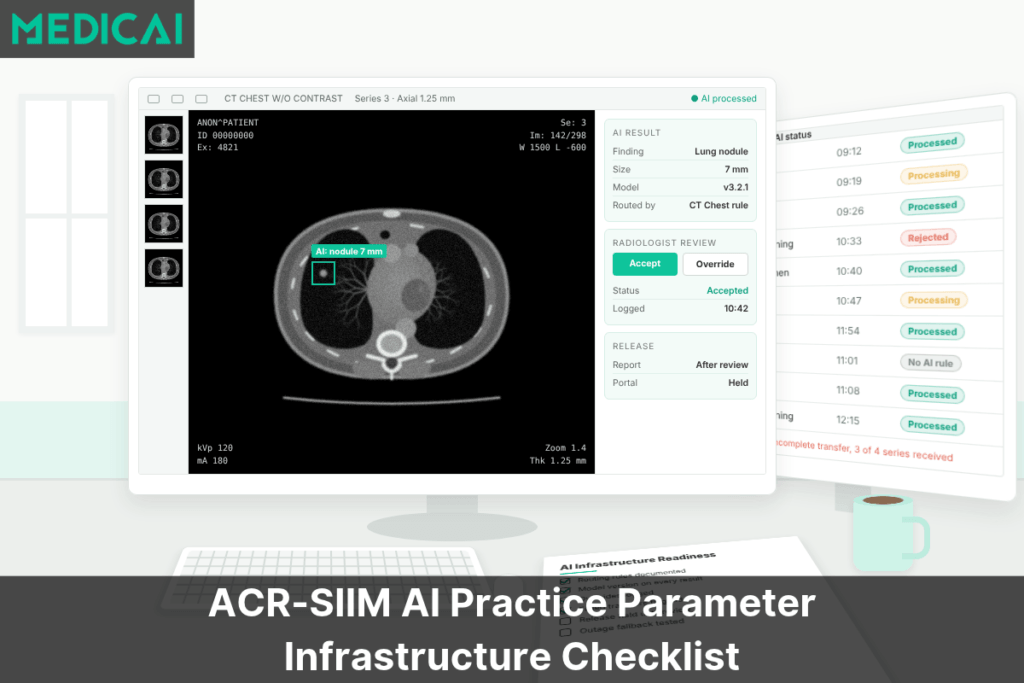
- Governance. The practice records which model version produced each result, is notified before the vendor updates the model, and checks performance on its own cases, as the 2026 ACR-SIIM practice parameter for imaging AI recommends.
On Medicai, steps 1 through 5 run through AI Integrations on the Enterprise plan; the model’s results display in the DICOM viewer next to the study, and the Radiology AI Co-Pilot then drafts from the radiologist’s dictation as usual. Ask us which models have been connected for the modality you read, and ask the model vendor for its DICOM output specification (SR template, overlay format) so the two can be checked against each other before contract.
The Integrated Cloud-Native Approach
The architectural alternative to multi-vendor integration is an integrated cloud-native infrastructure in which the worklist, PACS viewer, dictation interface, structured reporting, and report delivery operate as components of a single platform rather than as separately procured products with integration interfaces between them. Medicai’s cloud-native PACS on Microsoft Azure provides this integrated approach: the worklist is built into the platform, the zero-footprint browser-based DICOM viewer is the radiologist’s reading workstation, structured reporting templates integrate with the viewer through the platform’s reporting layer, and HL7 ORU and FHIR DiagnosticReport delivery are configured at the platform level rather than per product.
The integrated approach has trade-offs. It eliminates inter-vendor integration friction but requires the platform to match specialized single-product vendors’ capabilities. For radiology practices procuring new infrastructure or migrating from legacy on-premises PACS, the integrated approach typically deploys faster and costs less to integrate overall. For large hospital systems with established PowerScribe, MModal, or other enterprise dictation deployments, integration with existing products through standard interfaces is usually the practical path. See the Medicai cloud PACS for the underlying platform capabilities and the AI in radiology guide for the AI applications that integrate with the reading workflow at each stage.
On Medicai, the drafting step also happens within the platform: the Radiology AI Co-Pilot works in the same viewer, uses the same templates, and sends the signed report via HL7 ORU or FHIR DiagnosticReport, as described above.
Frequently Asked Questions
Radiology dictation software is software that combines voice recognition, structured reporting templates, report editing, and EHR delivery into a workflow tool that radiologists use to produce diagnostic reports from their dictation of imaging findings. The category includes enterprise integrated platforms such as Nuance PowerScribe and PowerScribe One (Microsoft) and 3M MModal Fluency for Imaging (Solventum); AI-first reporting platforms such as Rad AI Reporting and Impressions, MD.ai, and rScriptor; and standalone dictation tools such as VoiceboxMD. The software typically integrates with the radiologist’s PACS viewer for image review context and with the EHR for report delivery through HL7 ORU or FHIR DiagnosticReport messages.
The right radiology dictation software depends on practice size, existing PACS and RIS infrastructure, budget, and clinical use case. Nuance PowerScribe and PowerScribe One are the de facto US market standard for enterprise radiology reporting, used by the majority of US hospital radiology groups, with broad PACS compatibility and high voice recognition accuracy on radiology vocabulary. 3M MModal Fluency for Imaging (now under Solventum) is the second major enterprise platform with stronger NLP-based structured data extraction features. Rad AI Reporting and Impressions are the leading AI-first platforms, often deployed alongside an existing enterprise platform to add AI-drafted impression sections rather than replacing the dictation engine. For small practices and independent radiologists, VoiceboxMD and rScriptor offer per-seat or per-practice pricing alternatives to enterprise contracts. No single product is “best” for all use cases; the procurement decision should follow a structured evaluation of practice-specific requirements.
Radiology voice recognition uses speech recognition engines trained on large corpora of radiology dictation to accurately transcribe spoken findings into structured text. The engine recognises radiology-specific vocabulary (anatomy terms, pathology terms, classification phrases like BI-RADS or Lung-RADS), routes content to the appropriate section of structured report templates, and extracts measurements and other structured data points automatically. Modern radiology voice recognition operates in real time during dictation rather than batch processing later, with vendor-reported accuracy typically exceeding 99% word accuracy for trained users on radiology dictation. The newest generation of dictation software extends beyond transcription into AI-drafted report generation, where the AI generates draft report content from the imaging study itself and the radiologist reviews and edits using voice commands.
The leading radiology voice recognition systems are Nuance PowerScribe and PowerScribe One (Microsoft), the de facto US enterprise standard, and 3M MModal Fluency for Imaging (Solventum), both combining radiology-trained voice recognition with structured reporting and EHR delivery. Nuance Dragon Medical One is the cross-specialty clinical voice recognition engine often used alongside them. Among AI-first systems, Rad AI leads by drafting report content that the radiologist edits by voice. The right system depends on practice size, existing PACS and RIS, and whether the goal is enterprise-wide reporting or AI-assisted drafting; there is no single best system for every practice.
A radiology worklist is the queue of imaging studies awaiting interpretation by a radiologist, displayed in the PACS, RIS, or dedicated worklist orchestrator. The worklist shows pending studies with their key metadata (patient identifier, modality, body part, ordering provider, priority, arrival time, subspecialty assignment) and allows the radiologist to select studies for interpretation. Modern worklists support filtering, sorting, subspecialty routing, multi-source aggregation across PACS and external sources, and AI triage prioritisation where suspected critical findings are moved to the top of the worklist before the radiologist opens any study. AI triage products including Viz.ai (stroke), Aidoc (multi-pathology), and RapidAI (stroke and pulmonary embolism) integrate with the worklist to provide this prioritisation.
Enterprise radiology dictation platforms (Nuance PowerScribe, 3M MModal Fluency for Imaging) are typically sold under negotiated enterprise contracts with pricing that varies significantly by practice size, radiologist count, integration scope, and contract terms. Annual subscription costs for enterprise platforms typically range from $1,500 to $4,000 per radiologist per year, with additional one-time integration costs of $25,000 to $150,000 depending on PACS, RIS, and EHR integration scope. AI-first reporting platforms (Rad AI, MD.ai) typically add per-radiologist or per-study fees on top of an existing enterprise platform rather than replacing it. Standalone dictation tools (VoiceboxMD, rScriptor) offer per-seat subscription pricing typically in the range of $100 to $400 per radiologist per month, making them economically viable for small practices and independent radiologists.
Radiology dictation software integrates with the PACS through several technical interfaces. Worklist integration uses HL7 ORM messages from the RIS or DICOM Modality Worklist queries to populate the radiologist’s reading queue. Image viewer integration uses URL launch hooks or messaging APIs so that opening a study in the PACS viewer also opens the corresponding report template in the dictation software. Report delivery uses HL7 ORU messages for traditional EHR integration or FHIR DiagnosticReport for newer API-based integration. AI triage signals (Viz.ai, Aidoc, RapidAI critical finding alerts) reach the worklist through DICOM Structured Reports, HL7 messages, or vendor-specific APIs. The integration depth and quality varies widely across vendor combinations, and the radiologist’s productivity depends heavily on how well the integrated systems communicate. Modern cloud-native PACS platforms increasingly provide integrated dictation, structured reporting, and worklist management as part of the same platform, eliminating the inter-vendor integration complexity that defines legacy multi-vendor reading environments.
Several cloud PACS vendors now build drafting into the viewer; Medicai’s Radiology AI Co-Pilot drafts the report from dictation into the practice’s templates, drafts the impression, marks AI text in brackets, and runs a proofreading pass before signing; it does not summarize priors or analyze images. None of these drafting functions, from any vendor, is what FDA clears: clearance applies to image-analysis functions (detection, triage, quantification) for stated indications. Ask any vendor claiming a cleared reporting tool which function the clearance covers and for the 510(k) number.
Any cloud PACS that can route studies by rule to an external DICOM node and display returned DICOM SR and overlay objects in its viewer. The study is sent to the model as it arrives; the model returns findings as DICOM objects attached to the study, and the radiologist sees them in the viewer before dictating. On Medicai, this runs through AI Integrations on the Enterprise plan, with routing set in the DICOM Gateway; the model’s clearance (Lunit INSIGHT MMG is FDA 510(k) cleared and CE marked) belongs to the model vendor for its indication.
Medicai includes the Radiology AI Co-Pilot in its DICOM viewer: dictation becomes a structured draft in your templates, and the radiologist reviews and signs every report. A practice already on PowerScribe or Fluency can keep it and deliver reports to Medicai by HL7 ORU; a practice moving to Medicai from scratch does not need a separate dictation contract.

Related Articles
Lets get in touch!
Learn more about how Medicai can help you strengthen your practice and improve your patients’ experience. Ready to start your Journey?
Book A Free Demo